Search conditions, treatments, research reviews and articles. Press Enter to see all results, Esc to close.
Search conditions, treatments, research reviews and articles. Press Enter to see all results, Esc to close.
Blog
November 11, 2026
Blepharitis treatment controls the condition rather than curing it. The main treatment is daily lid hygiene: warm compresses and gentle cleaning of the lash line. Most people need to keep that routine going long term, because blepharitis usually does not go away completely [1,2]. When lid hygiene is not enough, an eye doctor can add antibiotic or steroid drops or ointment, oral antibiotics, a prescription drop for eyelash mites, or in-office treatment of the oil glands, depending on which type of blepharitis you have [2,3].
This guide is general education and does not replace an eye exam. A red, painful eye with blurred vision or light sensitivity needs prompt care from an eye doctor.
Key takeaways
In this article
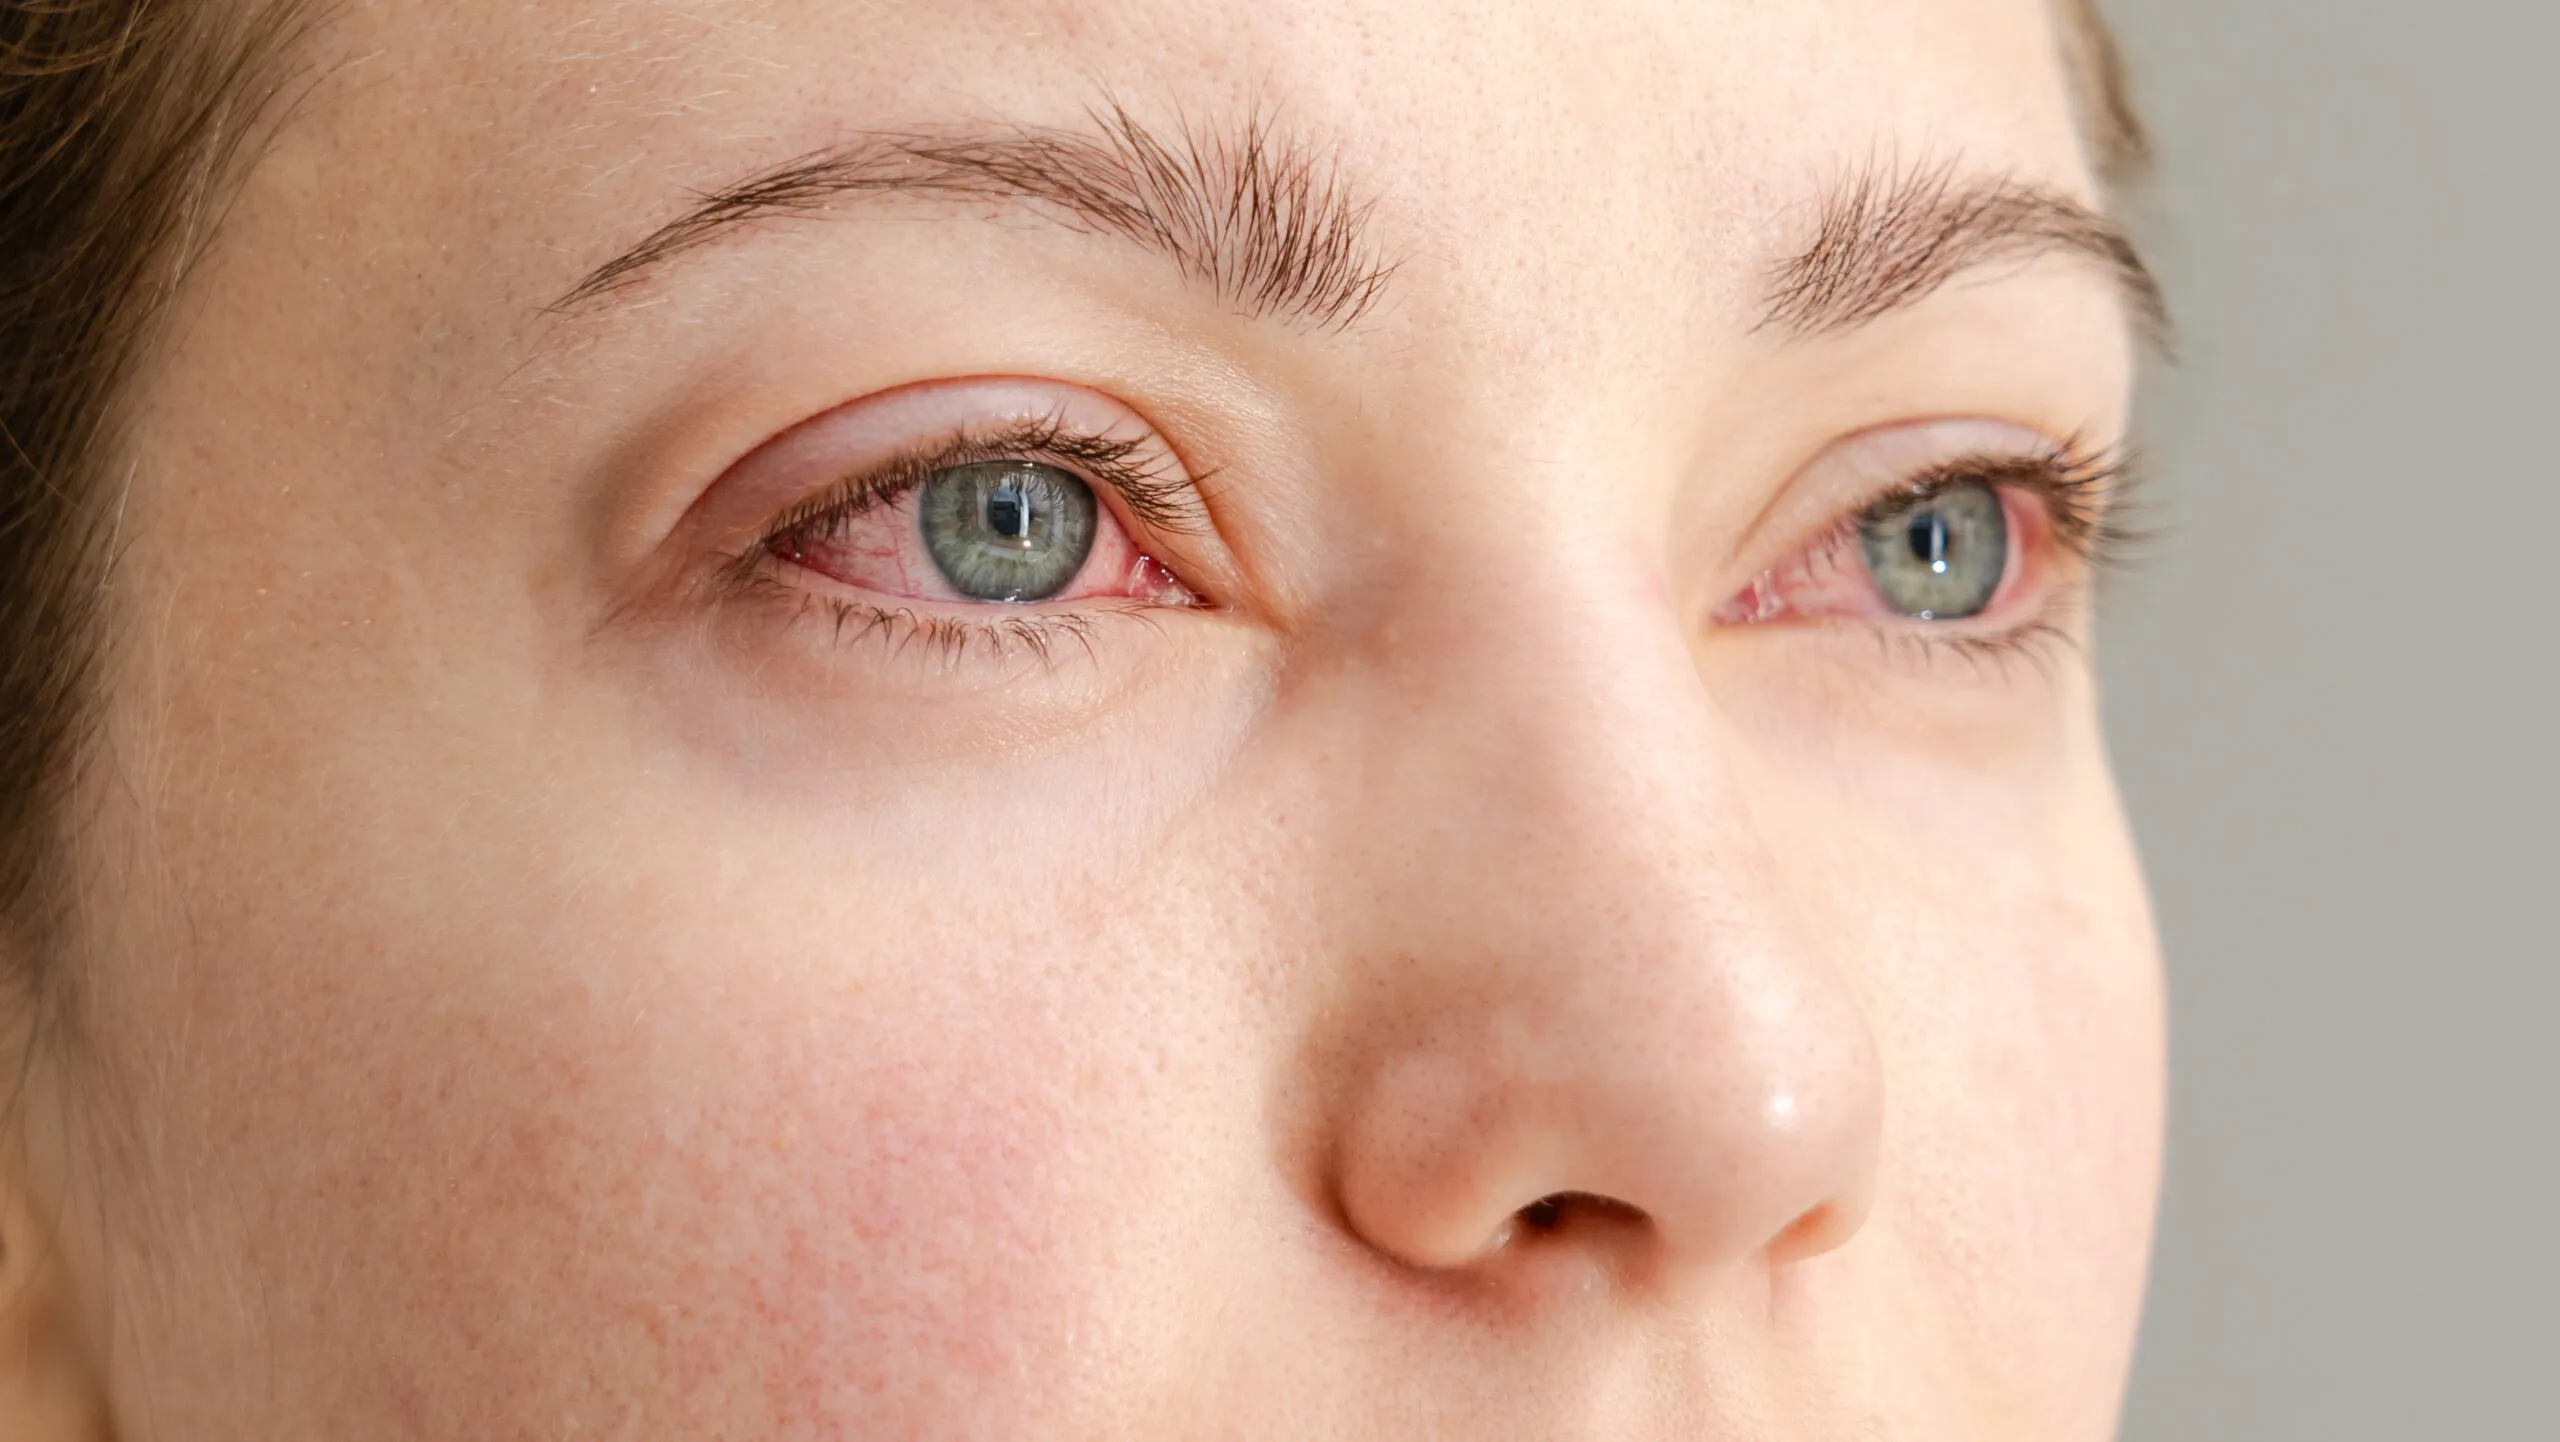
Blepharitis is inflammation of the eyelid edges. It makes the lids red, swollen, irritated and itchy, often with crusty, dandruff-like flakes on the lashes. It is not contagious and rarely causes lasting eye damage [1]. Treatment depends on where the inflammation sits, and many people have more than one type [1].
| Type | Where it is | What you may notice | Usual drivers |
|---|---|---|---|
| Anterior blepharitis | The outer lid edge, where the lashes attach | Crusts or flakes on the lashes, red lid edges, crusting on waking | Skin bacteria and scalp or eyebrow dandruff |
| Posterior blepharitis (meibomian gland dysfunction) | The inner lid edge, at the openings of the oil glands | Burning, a gritty or dry feeling, foamy tears, vision that blurs and clears with blinking | Clogged oil glands, often with rosacea or dandruff |
| Demodex blepharitis | The eyelash follicles | Itching and sleeve-like deposits (collarettes) at the base of the lashes | An overgrowth of eyelash mites |
Sources for the table: [1,5]. Our guide to Demodex blepharitis covers the mite type in detail, and ocular rosacea explains the skin condition that often drives oil-gland disease.
Every blepharitis plan starts here, whatever the type. In the Cochrane review, lid hygiene, including warm compresses and lid scrubs, eased symptoms of both anterior and posterior blepharitis [4].
Artificial tears can ease burning and dryness while lid hygiene takes effect [1,2]. If your eyes also feel dry most of the day, our guide to dry eye treatment explains the next steps.
If lid hygiene alone does not control symptoms, an eye doctor chooses a treatment based on the type and severity of blepharitis.
| Treatment | Mainly used for | What to know |
|---|---|---|
| Antibiotic ointment or drops | Anterior blepharitis with bacterial overgrowth | In trials, topical antibiotics eased symptoms and cleared bacteria from the lid edge [4]. Ointment is usually applied to the base of the lashes at bedtime [2]. |
| Steroid or antibiotic-steroid drops or ointment | Short-term control of redness and swelling | Steroids eased symptoms in trials but did not clear bacteria [4]. They need follow-up, because longer use can raise eye pressure [3]. |
| Oral antibiotics, such as doxycycline or azithromycin | Oil-gland disease and ocular rosacea | Used for their anti-inflammatory effect as well as against bacteria [3]. Oral azithromycin can cause heart rhythm problems in people with heart disease [3]. |
| Lotilaner 0.25% eye drops (XDEMVY) | Demodex blepharitis | Approved by the FDA in July 2023. One drop in each affected eye twice a day for 6 weeks. In the two main trials, 44% and 55% of patients had clear lashes at day 43, compared with 7% and 12% on an inactive drop [5]. |
| A prescription drop that mimics eyelid oil | Tears that evaporate too fast because of oil-gland disease | Helps keep the tear film from drying out [2]. |
| In-office gland treatments | Clogged oil glands that home care does not open | Devices that heat and massage the glands are done in the office by an eye doctor [2]. They treat the glands, not the bacteria or mites. |
Treatment that is not working deserves a second look rather than more of the same. The American Academy of Ophthalmology advises that blepharitis that does not respond to treatment, especially with eyelash loss or scarring of the eye surface, should prompt a check for an eyelid cancer or an immune-related disease [3].
Blepharitis cannot be cured quickly, and in most people it cannot be cured at all [2,4]. A flare can be brought under control, though, and these steps give it the best chance:
Online stories of a cure are usually stories of control. The person has often found the treatment that matched their type, such as a mite treatment for Demodex or heat and gland care for oil-gland disease, and kept up a daily routine. That is worth copying. What usually does not last is the cure itself: blepharitis tends to come back when the routine stops [1].
Read these stories with two questions in mind. First, does the remedy go on the eye or lid edge? If so, it should be a product made for that use. Second, did the person also see an eye doctor? Many successful stories involve a prescription alongside the home routine.
| Remedy | What the evidence shows | Our view |
|---|---|---|
| Warm compresses | Recommended by the National Eye Institute and the American Academy of Ophthalmology. Part of the lid hygiene that eased symptoms in trials [1,2,4]. | Use daily. |
| Lid cleaning with diluted baby shampoo | A long-standing recommendation from both organizations [1,2]. | Fine to use. Switch to an eyelid cleanser if it stings. |
| Hypochlorous acid 0.01% lid cleansers | Small randomized trials over 2 to 4 weeks found better symptoms or lid signs than saline scrubs or hyaluronic acid wipes, and lower bacterial counts [7,8]. | A reasonable option. Use products made for the eyelids. |
| Tea tree oil | Used against eyelash mites, but a Cochrane review rated the evidence uncertain. Some people had eye irritation, and the review suggested lower concentrations [6]. | Only as low-strength products made for the eyelids. Never put undiluted essential oil near the eye. |
| Omega-3 fish oil | In the DREAM trial, 3,000 mg a day for 12 months did no better than an olive oil placebo for dry eye [9]. | Fine as part of a healthy diet. Do not count on supplements to treat blepharitis. |
| Treating dandruff and rosacea | The National Eye Institute lists treating these underlying conditions as part of care [1]. | Worth doing. |
| Tea bags, coconut oil and homemade eye washes | No reliable trials for blepharitis. Home preparations are not sterile. | Avoid putting homemade preparations on the eye or lid edge. |
Our guide to swollen eyelids lists other warning signs.
Netra Eye Institute does not diagnose blepharitis or prescribe the drops and pills above. Your eye doctor does. When blepharitis comes with long-standing dry eye, Netra's integrative care is offered alongside that plan, never instead of it. We do not recommend herbal oils or homemade preparations on the lid edge. Learn more about dry eye care at Netra.
No. Blepharitis is not contagious [1].
Usually for years, with flares that come and go. It rarely goes away completely, which is why a daily lid routine is recommended long term [1,2].
A flare can settle, but the tendency usually remains. Symptoms often return when lid hygiene stops [1].
The fastest route is the treatment that matches your type, started early and used every day. For bacterial blepharitis that may be an antibiotic ointment with lid hygiene. For eyelash mites it is a 6-week course of lotilaner drops [4,5]. Your eye doctor can tell which type you have.
Rarely. Blepharitis usually does not cause lasting damage, but severe or untreated cases can affect the cornea, the clear front of the eye [1,4]. Blurred vision that does not clear with blinking should be checked.
Either is reasonable. Diluted baby shampoo is a long-standing recommendation [1,2]. Hypochlorous acid cleansers have small trials showing benefit and may sting less [7,8].
No. It is used against eyelash mites, but the evidence is uncertain and it can irritate the eye [6]. If you use it, choose a low-strength product made for the eyelids.
Sources checked November 11, 2026.
This article provides general education and does not replace an individual eye examination, diagnosis or treatment plan. Do not stop prescribed treatment without your eye doctor. Seek prompt care for eye pain, light sensitivity or blurred vision that does not clear with blinking.