Search conditions, treatments, research reviews and articles. Press Enter to see all results, Esc to close.
Search conditions, treatments, research reviews and articles. Press Enter to see all results, Esc to close.

Blog
October 29, 2026
Scleral lenses are large, rigid gas-permeable contact lenses that vault over the cornea and rest on the tissue over the white of the eye. A reservoir of sterile, preservative-free fluid fills the space beneath the lens. This design can improve vision from an irregular cornea and protect selected diseased ocular surfaces, but it requires specialist fitting, careful hygiene, and ongoing monitoring. [1]
The benefits are easiest to understand by separating two goals: improving the optical surface and improving the environment over the cornea. Some patients need mainly visual correction; others need surface protection; many need both. A successful fit must also be manageable in everyday life.
Scleral lenses do not stop every underlying disease. They do not independently halt progressive keratoconus, cure autoimmune dry eye, reverse retinal damage, or replace treatment for active infection. NRT may be considered for selected accompanying symptoms and systemic contributors, while the fitting specialist remains responsible for lens design and safe wear.
In this article
The cornea normally provides a smooth surface that helps focus light. When its shape is irregular, glasses may be unable to correct the resulting distortions fully. A scleral lens creates a more regular front optical surface, while the fluid beneath it helps mask some of the corneal irregularity.
The lens also shields the cornea from direct eyelid friction during wear. Its fluid reservoir can be useful when an exposed or severely dry surface needs protection. However, a fluid reservoir is not a substitute for treating every cause of surface disease, and it is not a reason to leave a poorly fitting lens in place.
The landing area is over the sclera, but the lens interacts with the conjunctiva covering it. That tissue has its own contours, blood vessels, and sensitivities. The fitter must therefore evaluate more than the central corneal clearance. Pressure, alignment, movement, and the limbal region all contribute to comfort and safety. [1,2]
This explains why a lens that looks similar in a photograph may behave very differently on another eye. Scleral lenses are individually prescribed devices, not interchangeable accessories that can be selected by diameter or online reviews alone.
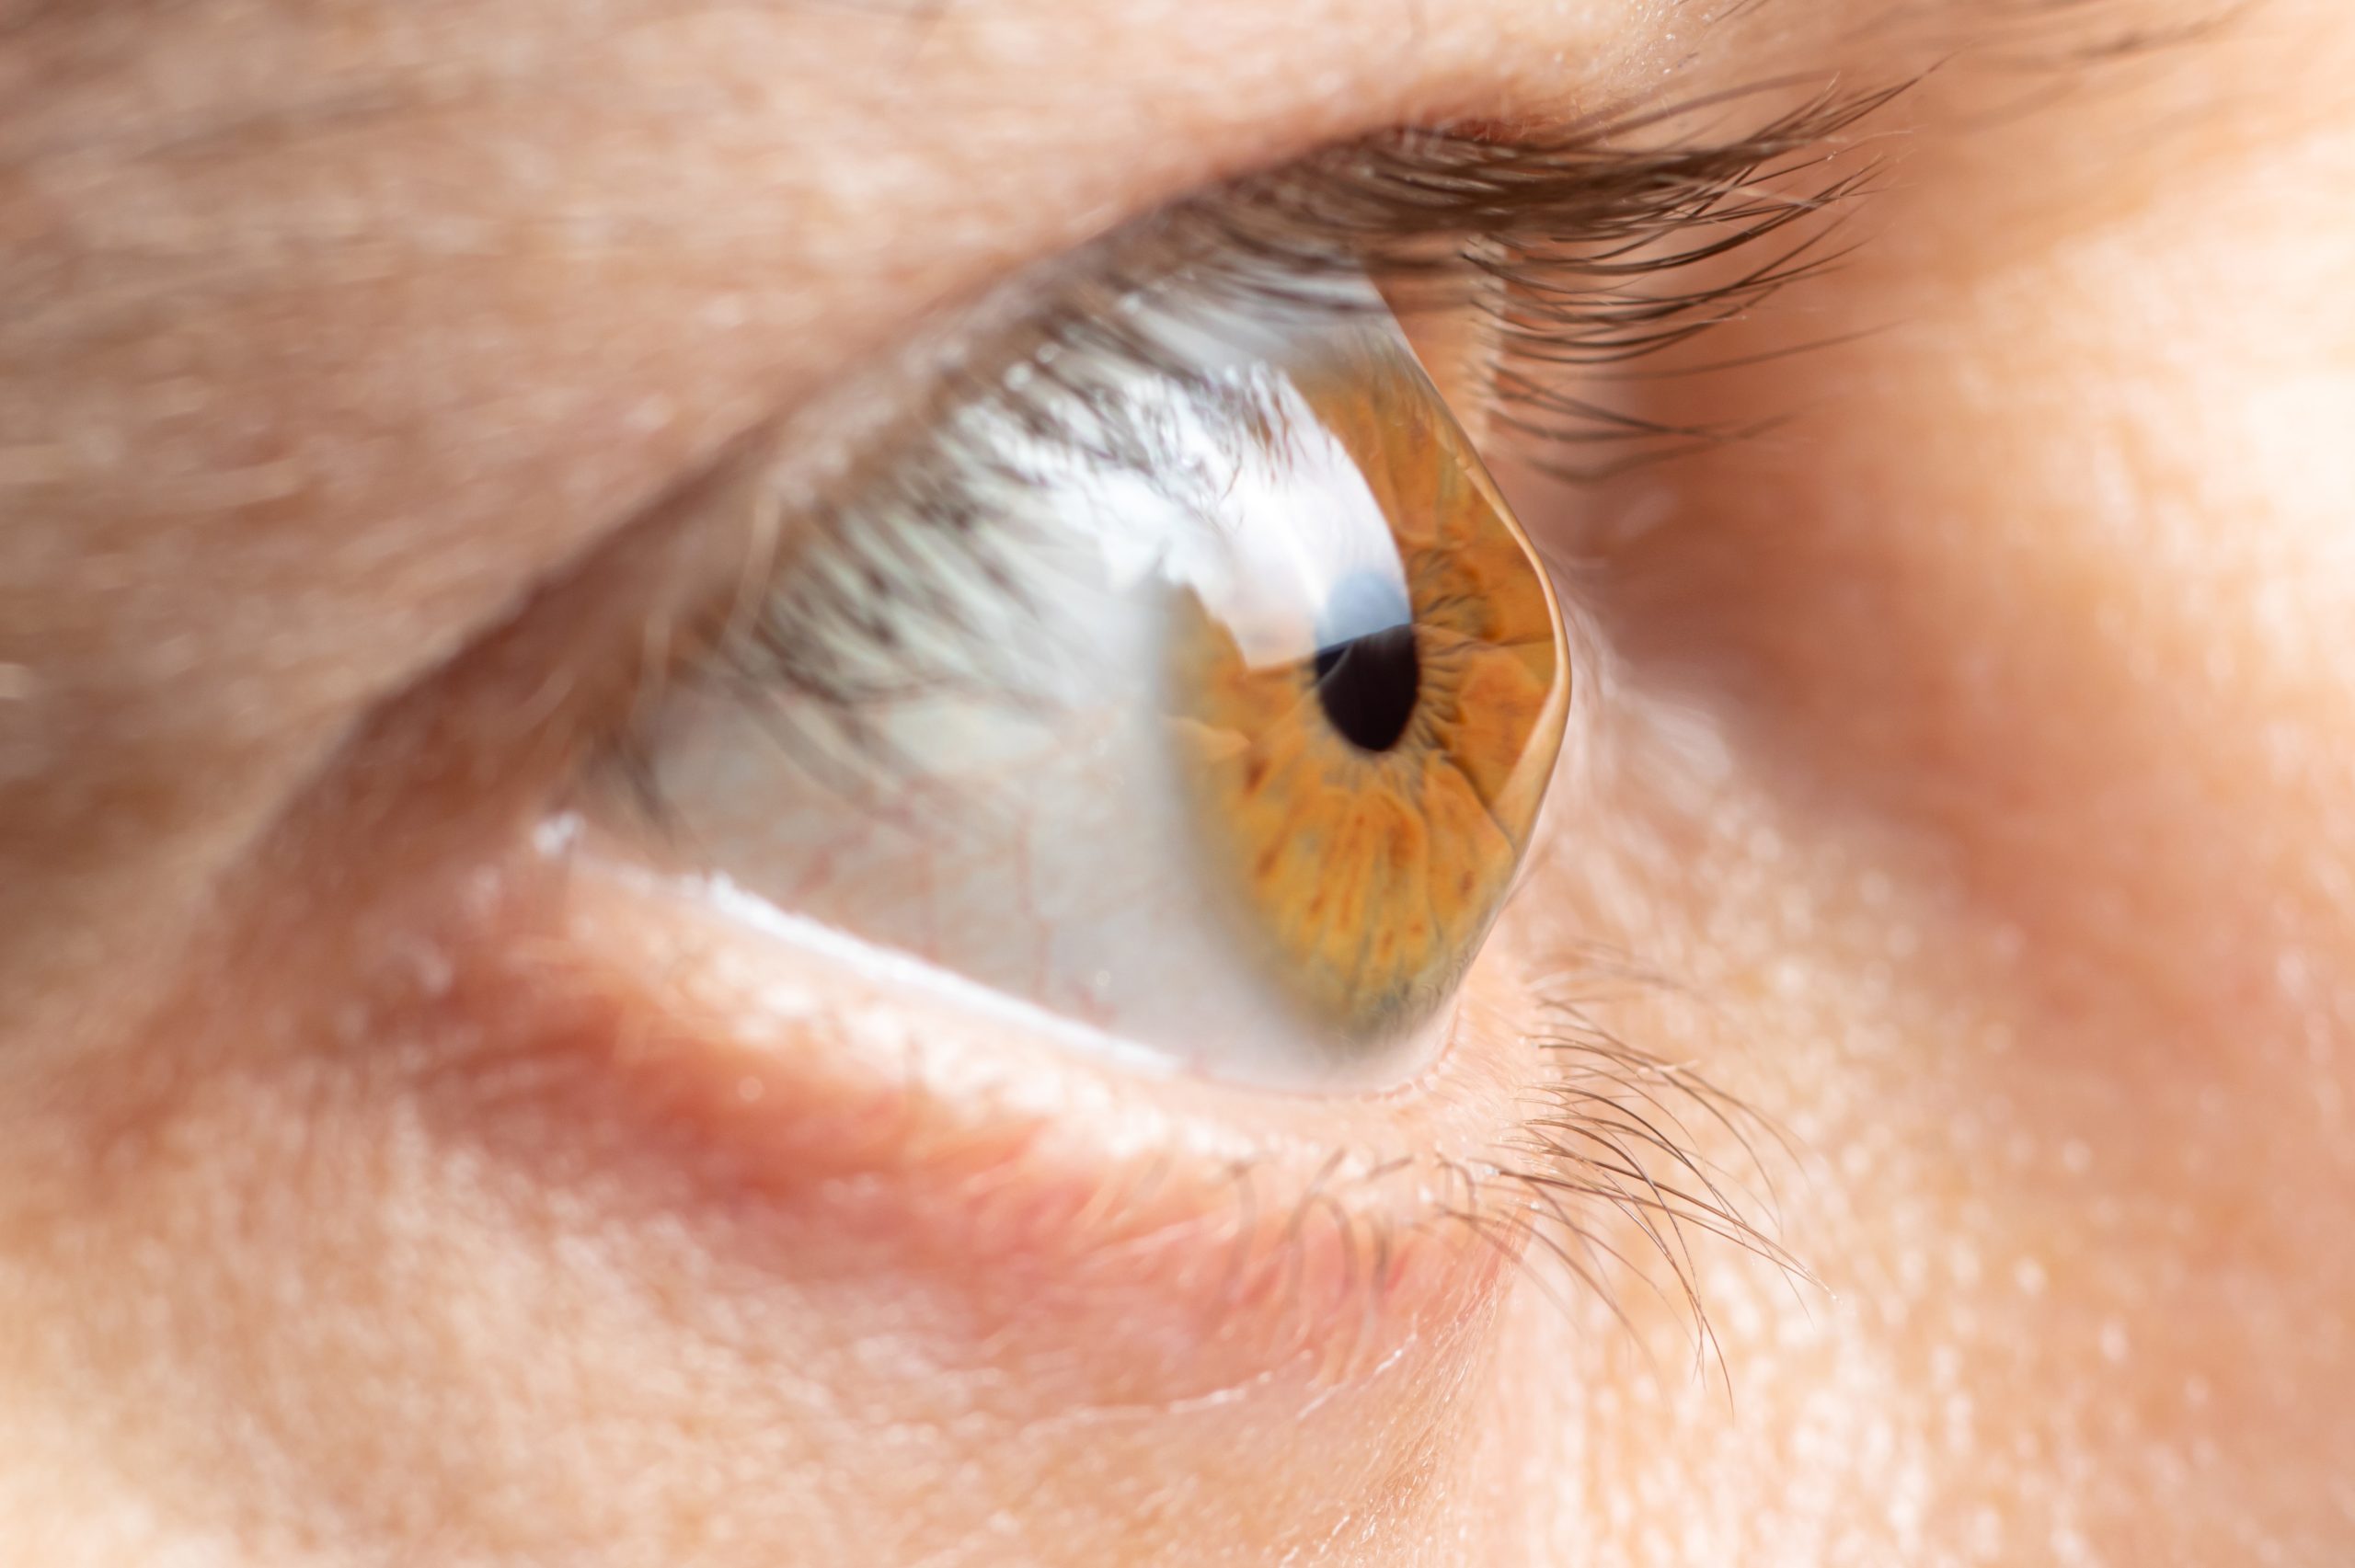
Keratoconus, some post-surgical corneal changes, and selected scars can produce irregular astigmatism. Scleral lenses may improve the optical problem when glasses or other lenses are inadequate or poorly tolerated. The improvement depends on how much of the visual limitation is due to the corneal surface rather than deeper eye disease.
For keratoconus, visual correction and disease stabilization are separate tasks. A comfortable scleral lens does not prove that progression has stopped. Continue the recommended corneal monitoring and discuss stabilizing treatment when indicated. Netra's keratoconus treatment guide explains how lenses fit within the wider treatment pathway.
Some patients with severe dry eye, exposure-related disease, or other chronic surface disorders benefit from the protected fluid environment. Candidacy depends on the diagnosis, surface integrity, infection risk, and ability to manage the device. Published evidence varies across conditions, with much of the literature consisting of clinical series rather than large randomized trials. [1,3]
The benefit should be defined in practical terms: improved reading, more comfortable activity, less friction, or a healthier surface during supervised care. A broad statement that scleral lenses “heal the eye” is too imprecise to guide an individual decision.
Failure of ordinary drops does not automatically make someone a candidate. The next question is why those treatments failed. Unrecognized inflammation, an exposure problem, severe aqueous deficiency, allergy, or neuropathic pain can require different strategies.
Some patients find the lens protective; others remain uncomfortable or cannot tolerate handling and wear. A fitting trial and follow-up are therefore part of determining benefit, rather than merely steps toward purchasing a device.
| Option | Main strength | Important consideration |
|---|---|---|
| Glasses | Simple daily use without touching the eye | May not adequately correct irregular corneal optics |
| Soft contact lenses | Useful for many ordinary refractive errors | May not sufficiently mask marked corneal irregularity |
| Corneal gas-permeable lenses | Can improve optics in selected irregular corneas | Comfort and fit depend on corneal interaction |
| Scleral lenses | Combine a regular optical surface with a fluid reservoir | Require individualized fitting, handling, and surface monitoring |
The most sophisticated option is not automatically the best one. A device should solve a problem that matters to the patient while remaining safe and usable. If glasses provide satisfactory vision and comfort, there may be no reason to add the complexity of scleral lenses.
PROSE treatment is a particular specialist treatment system using customized prosthetic scleral devices. It should not be used as a synonym for every scleral lens. BostonSight describes PROSE as a coordinated treatment process delivered by specifically trained providers, with continued involvement of the patient's primary eye-care team. [4]
The fitting process combines assessment of the eye, optical testing, trial-device evaluation, and patient training. The number of visits varies with the condition and the complexity of the fit. A promised universal one-visit solution is not a useful expectation for a complicated ocular surface.
The specialist reviews diagnosis, surgeries, medications, previous lenses, and the main visual or comfort goal. Visual acuity and the health of the cornea, lids, and conjunctiva are assessed. Additional imaging or measurements may help characterize the cornea and surrounding shape.
Baseline findings are important because later blur or redness may come from the underlying disease, the lens, the solution, or a combination. Without a baseline, it is harder to judge what changed.
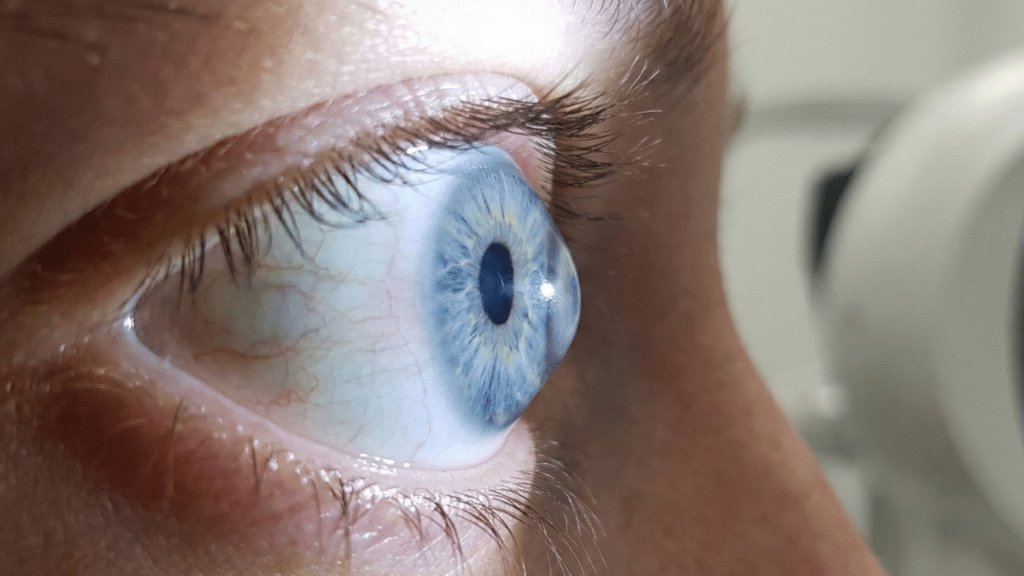
A trial lens is assessed for how it vaults the cornea and limbus and how its edge and landing zone interact with the conjunctiva. Clearance can change as the lens settles. The fitter may use slit-lamp examination and imaging to assess this relationship. [2]
Too much or too little clearance is not something a patient should try to correct by choosing a different device independently. The complete design, material, thickness, and eye condition affect what is appropriate.
The clinician checks whether additional optical correction improves clarity and whether the patient notices glare, ghosting, discomfort, or instability. A strong acuity result on a chart is valuable, but reading, driving, and sustained wear may reveal different problems.
Describe the experience precisely. Immediate blur can suggest a different issue from blur that develops after several hours. Localized pressure is different from generalized burning. These details help the fitter decide whether to change the design, examine the surface, or review the care products.
Training is a central part of treatment. The patient needs to demonstrate safe application, removal, cleaning, and recognition of problems. Dexterity, vision in the other eye, confidence, and the availability of a caregiver may affect the teaching plan.
The lens bowl must be appropriately filled, and a trapped bubble can interfere with vision or surface protection. If a bubble is present, follow the fitter's instructions for removal and reapplication rather than wearing the lens through the problem. Do not press forcefully on the eye or improvise removal techniques when the lens feels difficult to remove.
Follow-up should include the ocular surface with and without the lens and, when requested, an assessment after a representative period of wear. Bring the actual cleaning and filling products. A successful appointment depends partly on evaluating the routine the patient is really using, not the routine everyone assumes is being followed.
The most important distinction is between a solution that fills the lens for wear and a system that cleans and disinfects it after removal. They are not interchangeable. Sterile saline does not disinfect a lens simply because it is sterile when opened.
For filling, use the sterile, preservative-free solution recommended by the fitting clinician and compatible with the device. The fluid remains against the cornea during wear, so an inappropriate product can cause sustained irritation or toxicity. Do not fill the lens with tap water, homemade saline, or a cleaning solution. [5]
For cleaning and disinfection, follow the instructions for the particular lens, coating, and care system. Use fresh solution and the appropriate case. Product changes should be discussed with the fitter, especially when a lens has a surface coating that may be damaged by an incompatible cleaner.
Hydrogen peroxide can be part of a prescribed disinfection system, but unneutralized peroxide must never be placed in the eye or used as the filling fluid. The correct case and the full labeled neutralization time are essential. Do not shortcut the process because you are in a hurry or because the lens has been briefly rinsed. [6]
Keep peroxide clearly distinguished from filling saline and other bottles. A familiar-looking container is not enough to identify a product safely. If an accidental exposure causes pain, follow urgent professional advice rather than putting the lens back in to see whether the sensation settles.
Remove lenses for swimming, showering, and other water exposure unless a specialist has given a specific alternative plan. Water can contain organisms associated with severe keratitis. Neither clear-looking tap water nor distilled water is an appropriate substitute for the prescribed lens-care products. [7]
Clean hands and appropriate drying are part of the routine, as are care of the case and handling tools. Avoid topping off old solution. Carry a workable backup plan for a lens that must be removed away from home, including glasses where they provide useful vision. [8]
Wearing time should be prescribed individually. Comfort does not establish adequate oxygen delivery or guarantee that the surface is healthy. Some patients tolerate lengthy daytime wear, while others need shorter periods, breaks, or a revised fit.
Routine sleeping in scleral lenses should not be assumed safe. Specialized overnight therapeutic protocols exist in selected settings, but those are different from ordinary daily wear and require explicit supervision. The presence of fluid under the lens does not eliminate infection or oxygen-related risk.
Ask how to time prescription drops around wear. A drop placed on the front of a scleral lens may not reach the cornea in the same way as a drop applied directly to the eye. Do not add medications, serum tears, or other products to the reservoir without a specific instruction from the treating clinicians. [1,4]
Midday fogging describes debris collecting in the fluid reservoir during wear. The person may notice a gradual haze that improves after appropriate removal, cleaning, and refilling. However, fogging is not the only explanation for worsening vision in a lens.
Deposits on the front surface, poor wettability, an optical problem, or corneal edema can also cause blur. A review of midday fogging emphasizes examining the lens and eye to distinguish these possibilities. Treating every episode as harmless reservoir debris can miss a more important problem. [9]
The fitter may review the landing-zone alignment, clearance, ocular-surface inflammation, allergy, meibomian disease, or filling solution. Adjustments should follow the findings rather than an online recipe that assumes the same cause in every wearer.
Record when the blur begins, whether it is associated with redness or pain, whether refilling changes it, and whether it occurs in one or both eyes. Sudden blur or blur with pain deserves prompt assessment rather than routine troubleshooting.
Gas-permeable materials allow oxygen movement, but the lens and the fluid reservoir still influence oxygen delivery. Material properties, thickness, clearance, and wearing time all matter. A randomized crossover study in young adult volunteers found more corneal swelling with a lower-oxygen-permeability scleral lens material. Results from those volunteers do not guarantee safety in an already compromised cornea. [10]
Patients with a corneal graft, Fuchs dystrophy, or reduced endothelial reserve may require particular caution and monitoring. The endothelium helps maintain corneal clarity by controlling hydration. If swelling develops, the solution may involve a different fit, material, wearing schedule, or a decision that lens wear is unsuitable.
Do not use subjective comfort as the only measure of success. An eye can feel acceptable while developing clinically relevant swelling. Netra's Fuchs dystrophy guide provides background on why endothelial function matters.
NRT and a scleral lens address different aspects of care. The lens provides an optical and protective device; an NRT consultation may assess selected accompanying symptoms, daily exposures, and systemic contributors. NRT should not be presented as a replacement for fitting expertise or as a method of making an unsafe lens safe.
Netra's NRT overview describes an individualized adjunctive program. For a lens wearer, a sensible application begins by asking what problem remains after the fit and underlying disease have been assessed. Persistent discomfort should not automatically be attributed to stress or inflammation before mechanical, infectious, and oxygen-related causes are considered. [11]
The goal might be improved comfort outside lens-wearing hours, better adherence to an established surface routine, or more manageable daily symptoms in a stable eye. These are different from increasing wearing time. Longer wear is not a successful outcome if the eye becomes redder, swollen, or less healthy.
A shared plan can record comfortable wear time, reading tolerance, need for removal, and the fitter's findings. It should also document solution changes and lens modifications. Otherwise, an improvement after refitting might be incorrectly attributed to an adjunctive intervention introduced at the same time.
Some dry-eye trials have found improvements in selected symptom and tear measures with acupuncture, while other outcomes have not differed from comparison treatment. This evidence does not establish that NRT prevents scleral-lens fogging, improves lens fit, or increases safe wearing time. [12]
Where appropriate, an adjunctive trial should have a specific outcome and a planned reassessment. A patient whose main problem is fogging still needs a fitting and surface evaluation; a patient with a painful red eye needs prompt medical assessment. Complementary care should not become an explanation that delays either.
The fluid reservoir is not a place for herbal preparations, oils, ghee, or unprescribed drops. Any ingredient placed there may remain against the cornea for hours and may interact with the lens or coating. Follow the fitter's filling instructions even if a product is described as nourishing or natural. [5,13]
If a traditional ocular procedure is proposed outside lens wear, its suitability must be assessed separately. Active infection, epithelial defects, and recent surgery require the boundaries described in Netra's co-management guidance. Removing a lens temporarily does not remove those underlying contraindications. [14]
The fitting clinician should know about adjunctive treatments and any change in symptoms. The NRT team should have the relevant diagnosis, recent surface findings, and restrictions. The treating ophthalmologist remains involved when the underlying disease requires medical or surgical management.
This division of responsibility helps the patient understand who to contact. Fit and handling questions go to the lens team; acute pain or visual change needs urgent eye care; a stable adjunctive goal can be discussed at a planned Netra consultation. Clear communication reduces the chance of receiving contradictory instructions.
Ask for an itemized quotation covering the evaluation, devices, training, revisions, follow-up, and replacement policy. A quoted lens price may not include the entire fitting process. Cleaning products, filling solutions, cases, and replacement devices are ongoing expenses.
Coverage can depend on diagnosis, medical necessity, provider arrangements, and the insurance plan. BostonSight's PROSE service, for example, describes medical-insurance assessment as part of its intake process; this should not be assumed to apply identically to every scleral-lens provider. [15]
If travel or hand function is a concern, discuss it before committing to treatment. A technically excellent device is useful only if the person can apply, remove, and care for it reliably or has adequate assistance.
No. They can improve vision by creating a more regular optical surface, but they do not independently stop disease progression. Continue corneal monitoring and discuss stabilizing treatment when indicated. Better vision in the lens should not be used as evidence that the underlying corneal shape is stable.
They can help selected patients by maintaining a protected fluid environment over the cornea. Candidacy depends on the cause, surface condition, and ability to manage the device. A lens may be one component of care while anti-inflammatory treatment, gland care, or systemic evaluation continues. [1,3]
Use only the sterile, preservative-free filling solution recommended by the fitter. Not every saline product is suitable, and saline used for filling does not replace disinfection. Do not use homemade saline, tap water, or a cleaning solution as a substitute. [5]
Do not sleep in them unless you are in a specifically prescribed and monitored therapeutic protocol. Ordinary daily-wear lenses are removed for sleep. A comfortable eye or a fluid-filled reservoir does not eliminate the risks associated with prolonged or overnight wear.
Reservoir debris, front-surface deposits, fit, or corneal swelling may be responsible. The fitter should examine the lens and eye to determine the cause. Blur with pain, redness, or a sudden change needs prompt assessment and should not be treated as routine midday fogging. [9]
Only if the prescribing and fitting clinicians specifically instruct you to do so. Serum tears have preparation, storage, contamination, and dosing requirements. Adding them to a reservoir changes how they are used and should not be improvised because both therapies are used for surface disease. Netra’s guide to autologous serum eye drops covers their preparation and storage.
That outcome should not be promised. NRT may be considered for an identified adjunctive goal, but it has not been established as a replacement for the optical correction or surface protection a scleral lens provides. Any change in wearing requirements should follow examination and discussion with the lens specialist.
Comfort and clear vision matter, but they are only part of the assessment. The specialist also evaluates clearance, landing-zone interaction, surface health, and the eye's response after wear. Persistent redness, pressure, pain, or blur should be reported even if the lens initially felt comfortable.
They may help selected patients with stable residual scarring or irregular optics after disease control. Timing and suitability require specialist assessment. A lens is not a treatment to start independently over an active ulcer or suspected infection, and monitoring remains important after fitting. See Netra’s guide to corneal ulcer healing.
Bring your lenses, cases, handling tools, filling and cleaning products, and medication list. Follow instructions about how long to wear the lenses before the visit. Describe when symptoms begin and how they change after removal, so the assessment reflects your real-world experience.
Sources checked October 29, 2026. Netra pages describe the provider’s approach; they do not independently establish treatment efficacy.
This article provides general education and does not replace an individual eye examination, diagnosis or treatment plan. Seek prompt clinical advice for new pain, a red eye with reduced vision or a significant visual change.