Search conditions, treatments, research reviews and articles. Press Enter to see all results, Esc to close.
Search conditions, treatments, research reviews and articles. Press Enter to see all results, Esc to close.
Blog
October 31, 2026
A diabetic vitreous hemorrhage is bleeding from fragile new blood vessels into the vitreous, the clear gel inside the eye. Some bleeds clear on their own, but dense ones often take months, and the vessels that bled still need treatment [1,2]. In the Protocol AB trial, the first bleed took a median of 36 weeks to clear with injections, compared with 4 weeks after vitrectomy surgery [3].
This article is general education. It does not replace advice from your own retina specialist.
Key takeaways
In this article
Any new bleed inside the eye needs prompt care from an eye doctor, ideally the same day. Go to an eye doctor or emergency room right away for a dark curtain or shadow, flashes of light, a sudden shower of floaters, or sudden vision loss. These can be signs of retinal detachment [1,5].
Do not drive yourself if your vision is poor. Our guide to urgent vision changes lists other eye symptoms that need same-day care.
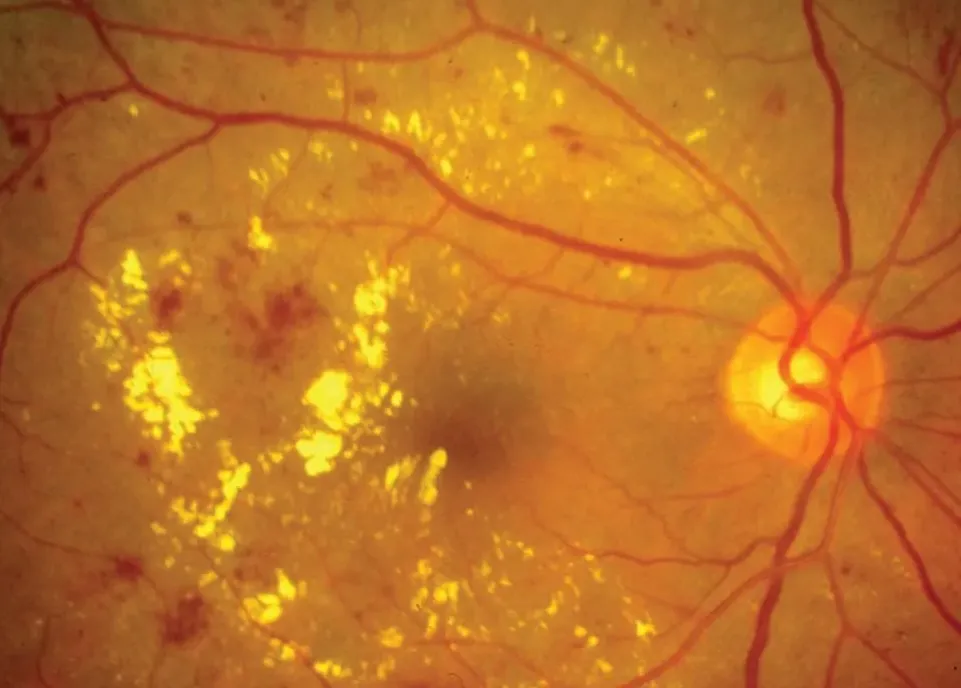
It is bleeding into the vitreous, the clear gel that fills the back of the eye. In diabetes it usually comes from fragile new vessels that grow in proliferative diabetic retinopathy (PDR). The blood can spread through the gel or collect in a pocket in front of the retina [1,8].
You may see dark floating spots, streaks that look like cobwebs, or a reddish haze [1]. A large bleed can block much of your vision. In Protocol AB, average starting vision was about 20/200 [4]. A bleed inside the eye is different from a red patch on the white of the eye. Only an eye exam can tell how much blood there is and where it came from.
Not every bleed in a person with diabetes comes from retinopathy. A posterior vitreous detachment, when the gel pulls away from the retina, can also cause bleeding. In a 2026 study of 366 such bleeds, 17% went on to retinal detachment, mostly in the first 3 weeks [9]. Read more about flashes, floaters and vitreous detachment.
Sometimes. A light bleed can thin out over weeks, but a dense bleed often takes months, and some never clear enough to see through. Even when the blood clears, the abnormal vessels can bleed again unless they are treated. Without treatment, scar tissue can also form [1,3,2].
The National Eye Institute notes that the spots sometimes clear on their own, but treatment should still start right away [1]. Clearing is not the same as cure. The new vessels behind the bleed are the real problem.
Short-term results can look reassuring. In the DRCR Protocol N trial, only 12% to 17% of eyes needed vitrectomy within 16 weeks [10]. But many eyes in longer studies take far longer to clear, as the next section shows.
There is no fixed timeline. In Protocol AB, eyes treated first with aflibercept injections took a median of 36 weeks for the first bleed to clear. The middle half of eyes took 24 to 52 weeks. Eyes that had vitrectomy cleared in a median of 4 weeks, because surgery removes the blood directly [3].
A median is the midpoint, so many eyes cleared faster and many slower. About one-third of eyes in each group also crossed over to the other treatment during the trial [3]. Your own timeline depends on how dense the blood is, whether it keeps returning, and whether scar tissue is present.
A 2024 review advises watching an eye with an attached retina for at least 4 weeks. If vision and the view do not improve, vitrectomy is then considered [2].
| Approach | What it does | When it is often used | Time to clear | Trade-offs |
|---|---|---|---|---|
| Watching plus laser when possible | Lets the body absorb the blood; laser treats new vessels once the view allows | Light bleed, attached retina, no worrying scar tissue | Varies from weeks to months | Vision stays blurred while waiting; bleeding can recur [1,2] |
| Anti-VEGF injections first | Calms the abnormal vessels; does not remove the blood | Attached retina without scar tissue near the macula | Median 36 weeks in Protocol AB | Repeat injections; about 1 in 3 later had vitrectomy [4,3] |
| Vitrectomy with laser | Removes the blood-filled gel; laser is applied during surgery | Dense or non-clearing bleed, scar tissue, detachment, very poor vision | Median 4 weeks in Protocol AB | Surgical risks, including cataract, new bleeding and detachment [3,2] |
Protocol AB compared aflibercept injections with prompt vitrectomy plus laser in 205 adults with a vitreous hemorrhage from PDR. Average vision over 24 weeks was not significantly different. Both groups averaged about 20/40 at 2 years. Vision recovered faster after surgery, and about one-third of each group later received the other treatment [4].
At 4 weeks, average vision was about 20/100 with injections and 20/63 with surgery [4]. The trial may have been too small to rule out a meaningful benefit from surgery, so "no significant difference" does not mean the two are identical [4].
A later analysis looked at eyes that started with very poor vision, worse than 20/800. In that group, vision over the first 24 weeks was much better with early vitrectomy [3]. People who had surgery first also reported less disruption of daily activities over 24 weeks, though the groups were similar by 2 years [11].
The trial did not include eyes with scar tissue detaching or threatening the macula, a retinal tear detachment, neovascular glaucoma, DME needing treatment, or past vitrectomy [12]. Its results apply best to eyes like those enrolled. As of October 2026, the trial authors' conclusion stands: both approaches are reasonable starting choices [3].
Vitrectomy is usually advised when the blood stays dense or keeps coming back, or when ultrasound shows scar tissue pulling on the retina or a detachment. It is also advised when laser cannot be completed, or when very poor vision makes waiting costly. Long-standing blood can also raise eye pressure, which may need early surgery [2,3].
Older evidence shaped today's practice. The Diabetic Retinopathy Vitrectomy Study randomized 616 eyes with severe bleeding and published 4-year results in 1990. Early surgery improved the chance of 20/40 vision in people with type 1 diabetes, but not in people with type 2 diabetes [13]. That trial came before modern small-incision tools and anti-VEGF drugs, so its waiting times are no longer applied as a rule [2].
Your fellow eye matters too. Tell your specialist if your other eye sees poorly, or if your work or safety depends on clear vision. These facts can tip the decision toward earlier surgery.
Many surgeons give an anti-VEGF injection a few days before vitrectomy. A 2023 Cochrane review of 28 trials found it probably lowered early bleeding after surgery, from 31% to 12%, and it cut retinal breaks during surgery [14]. In eyes with scar tissue, the injection is timed close to surgery, because it can make that tissue contract if surgery is delayed [2].
The surgeon removes the blood-filled gel through tiny openings in the eye wall and usually applies laser to the retina in the same operation. Most people go home the same day. The eye can stay red and blurry for several weeks, and many people take 2 to 4 weeks off work [15,2].
Our guide to injections, laser and surgery covers vitrectomy risks alongside other treatments.
Warning signs include a dark shadow or curtain over part of your vision, new flashes of light, and a sudden increase in floaters. With blood in the eye, these signs can be hard to notice, so any sudden drop in vision also counts. Retinal detachment is a medical emergency [5].
In diabetes, the retina can detach in two main ways. Scar tissue can pull it off (a tractional detachment), or a tear can let fluid get underneath (a rhegmatogenous detachment). When both happen together, vision can drop quickly, and early surgery is needed [2].
When blood blocks the view, a B-scan ultrasound helps find a detachment or scar tissue that the doctor cannot see directly [2]. Ask at each visit whether the retina is still attached.
Keep every follow-up visit, and do not wait out new symptoms at home. Keep taking prescribed medicines, including aspirin, unless your doctors advise otherwise. In the ETDRS trial, aspirin did not increase how often these bleeds happened, how severe they were, or how long they lasted [17].
For background on stages and treatment, see our diabetic retinopathy guide and the four stages of diabetic retinopathy.
Netra Restoration Therapy (NRT) is Netra Eye Institute's integrative program based on acupuncture and Oriental medicine, offered alongside care from eye doctors. NRT does not clear blood from the eye, does not treat the abnormal vessels, and cannot replace laser, injections or vitrectomy.
NRT has not been tested in controlled trials for diabetic vitreous hemorrhage. Never delay an exam, injection or surgery because of NRT. If you are curious about it, raise it with your retina specialist first. You can read what NRT involves and what is known about its effectiveness.
A new vitreous hemorrhage needs prompt care, ideally the same day, even if it starts to clear. It becomes an emergency if you also see a curtain, flashes or a sudden burst of floaters, because these can mean retinal detachment [1,5].
It can, but often vision returns once the blood clears or is removed. In Protocol AB, average vision improved from about 20/200 to about 20/40 at 2 years with either treatment. Lasting loss usually comes from linked problems such as retinal detachment, glaucoma or macular damage [4,1,2].
No eye drop is a standard treatment for a vitreous hemorrhage. The usual options are watching with laser, anti-VEGF injections into the eye, and vitrectomy surgery [1,2].
No. Anti-VEGF injections treat the abnormal vessels and can lower the chance of new bleeding, but the body still has to absorb the blood. In Protocol N, repeat bleeding within 16 weeks was 6% with ranibizumab and 17% with saline injections [10].
Neither is best for everyone. In Protocol AB, vision at 2 years was similar, but vitrectomy cleared the blood and improved vision faster, especially in eyes that started worse than 20/800. Injections avoided surgery for many eyes but took longer to work [4,3].
Not in the ETDRS trial. Aspirin at 650 mg a day did not increase the number, severity or length of vitreous bleeds in people with diabetic retinopathy. Do not stop or start aspirin without your doctor's advice [17].
Yes. A later bleed 3 or more months after diabetic vitrectomy affects about 10% to 20% of patients. Some clear on their own, while others need another washout or more laser [2].
Avoid waiting out new symptoms at home, driving with poor vision, and stopping prescribed medicines on your own. After vitrectomy with gas, do not fly or travel to high altitude until the bubble is gone, and warn any anesthetist about the gas [15,16].
Sources checked October 31, 2026.
This article provides general education and does not replace an individual eye examination, diagnosis or treatment plan. A new shower of floaters, flashes, a dark curtain or sudden vision loss in a person with diabetes needs same-day eye care; go to an eye doctor or emergency room right away.